Community mental health & CCBHCs
Multiple programs and locations under one set of standards, with state and certification requirements that change by county.
Solutions tuned to your organizational DNA, on one platform, from the front door to reimbursement. Onboard it like your best new hire, govern it like your team, and keep clinical judgment in charge.
Keep your EHR. Onboard intelligence.
Native across enterprise behavioral health, IDD, and SUD platforms, through a front-end integration that needs no EHR API.
























All product names, logos, and brands are property of their respective owners and are used for identification purposes only.
Forward-thinking customers











We’re hiring across engineering, clinical informatics, product, and customer success.
View Current Job Listings Life at Clinically AIGeneric AI behaves the same in every state and every county. Yours should not. Your policies, your payer and insurance contracts, your accreditation standards, your state and county requirements, and the verbiage your teams actually use are ingested once and sit underneath every product, so an agent already knows your organization before it does anything. Your systems, your regulations, your workflows. The solutions are built around them.
Configured by your leaders, audited by your team, accountable to you.
You define the gold standard for documentation quality. The platform applies it the same way across every program, every site, and every clinician.
Chart-aware and EHR-integrated. Every product works where your teams already work, writing into discrete and narrative fields in context.
Ask the platform why it wrote what it wrote. Every output traces back to the policy and the record behind it, auditable by your team.
The timing problem
Most organizations still review a small sample of charts days, weeks, or months after the service. By then the note is signed, the claim may be out, and the same pattern may have repeated across hundreds of records.
A five or ten percent chart review cannot reliably show what is happening across programs, locations, and EHRs. It was never designed to.
See audit risk as it happens, against configurable organizational, payer, regulatory, and program requirements, rather than weeks after the fact.
Identify inconsistencies and missing information earlier, see patterns across the enterprise, and address risk while it is still small.
Organizations can no longer afford to discover documentation risk only when a payer, regulator, or auditor finds it first.
On the phone in their pocket
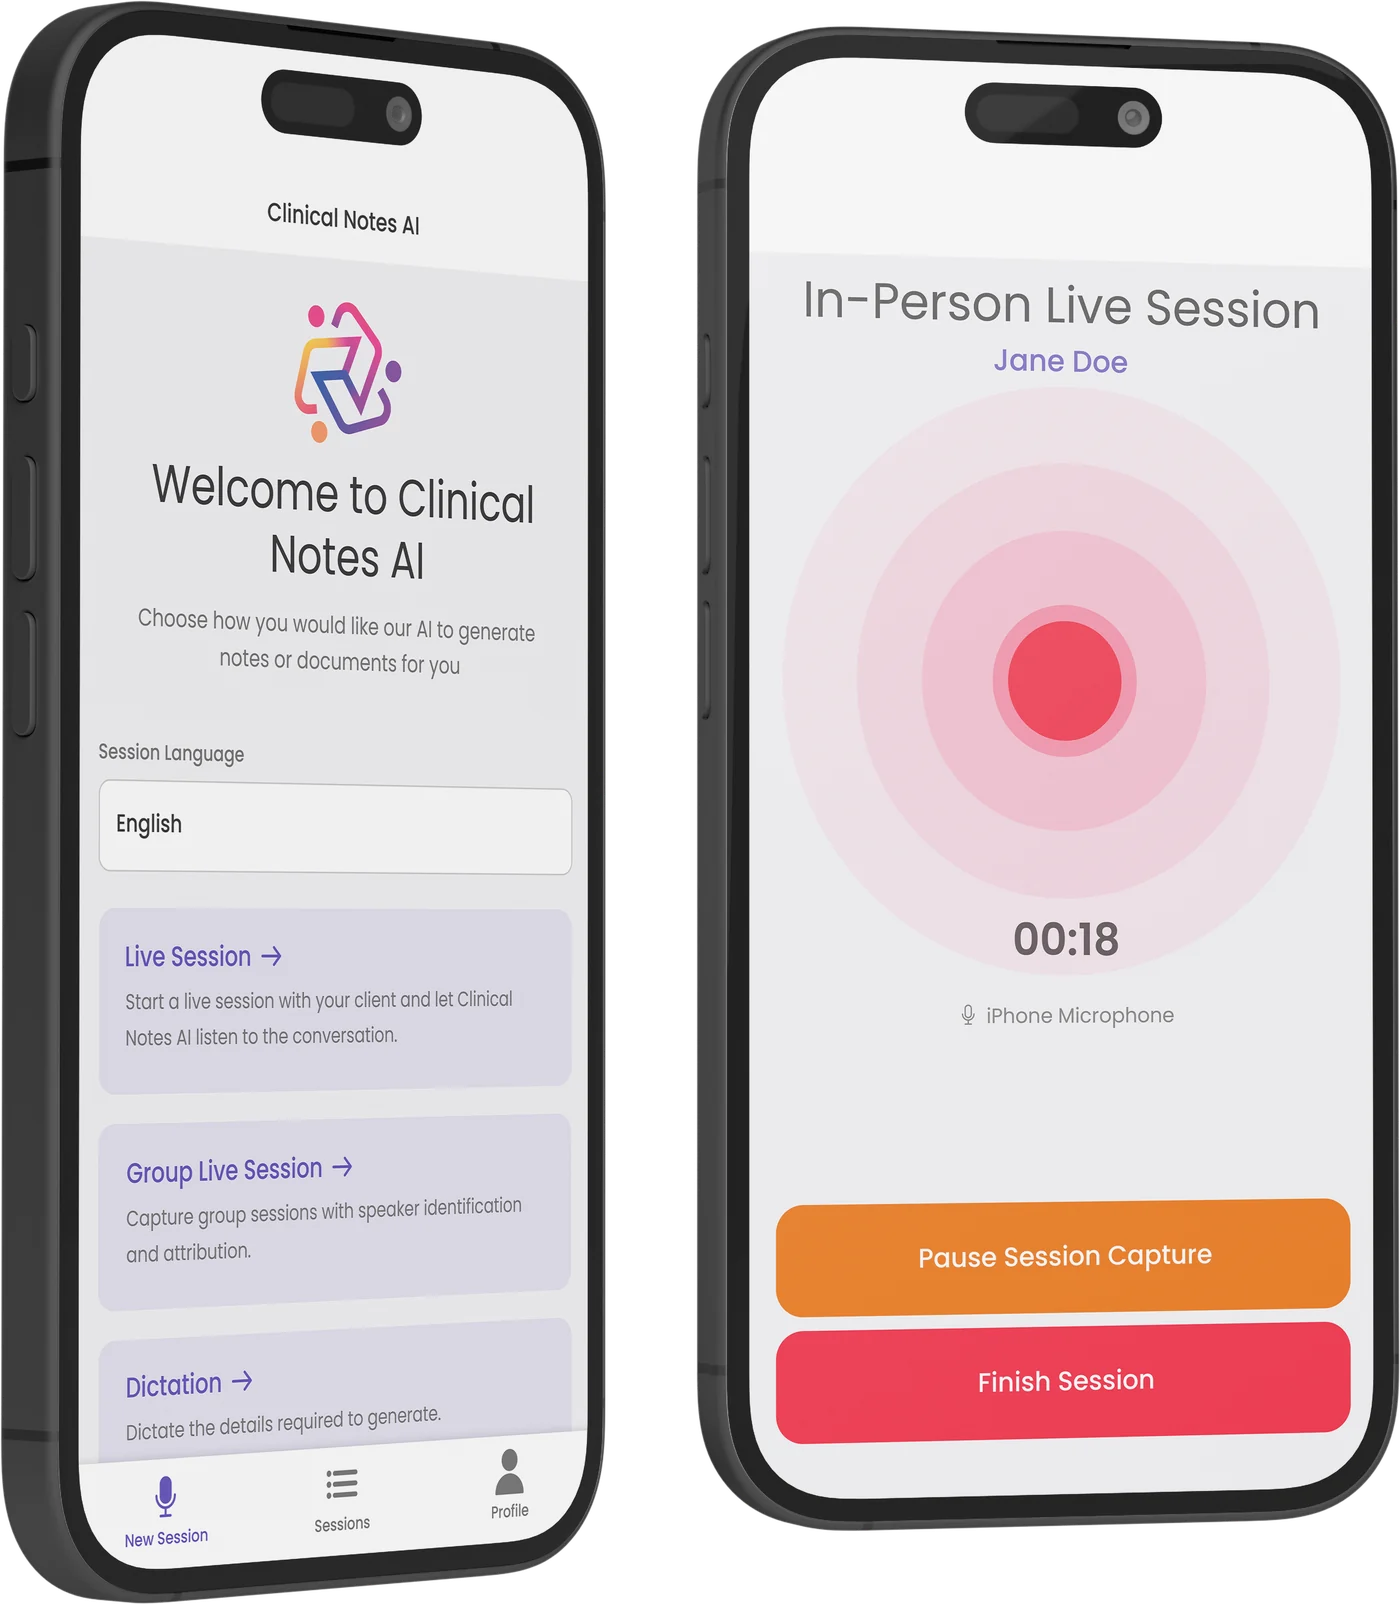
Crisis teams, mobile outreach, school-based services, home visits. The mobile app captures the session where the session actually happens, including group sessions and places with no signal.
Communities we serve
Behavioral health is not one workflow. Each of these communities documents differently, answers to different requirements, and breaks in a different place. The platform is configured for that, not around it.
Multiple programs and locations under one set of standards, with state and certification requirements that change by county.
Documentation that has to happen in a car, a home, or an ER bay, often with no reliable signal and no desk in sight.
Group-heavy caseloads, 42 CFR Part 2 handling, and medical necessity that has to hold up across levels of care.
Long service histories, waiver documentation, and support plans that span years rather than episodes.
Collateral contacts, guardian involvement, and services delivered in classrooms and living rooms.
Shift-based teams documenting continuously against utilization review and length-of-stay pressure.
High volume, tight turnaround, and payer rules that differ at every step down in intensity.
Care plans assembled from many hands, where the golden thread has to survive every handoff.
“I can focus on my engagement with patients, not juggling typing while talking.”Psychiatric Provider, West Michigan Community Mental Health
What customers say
Named, attributed, and from organizations running this at scale.
“If we said, sorry, we’re going to take it away now, I think there would be mutiny.”
“If the solution were removed tomorrow, our clinicians would be devastated.”
For the people accountable for it
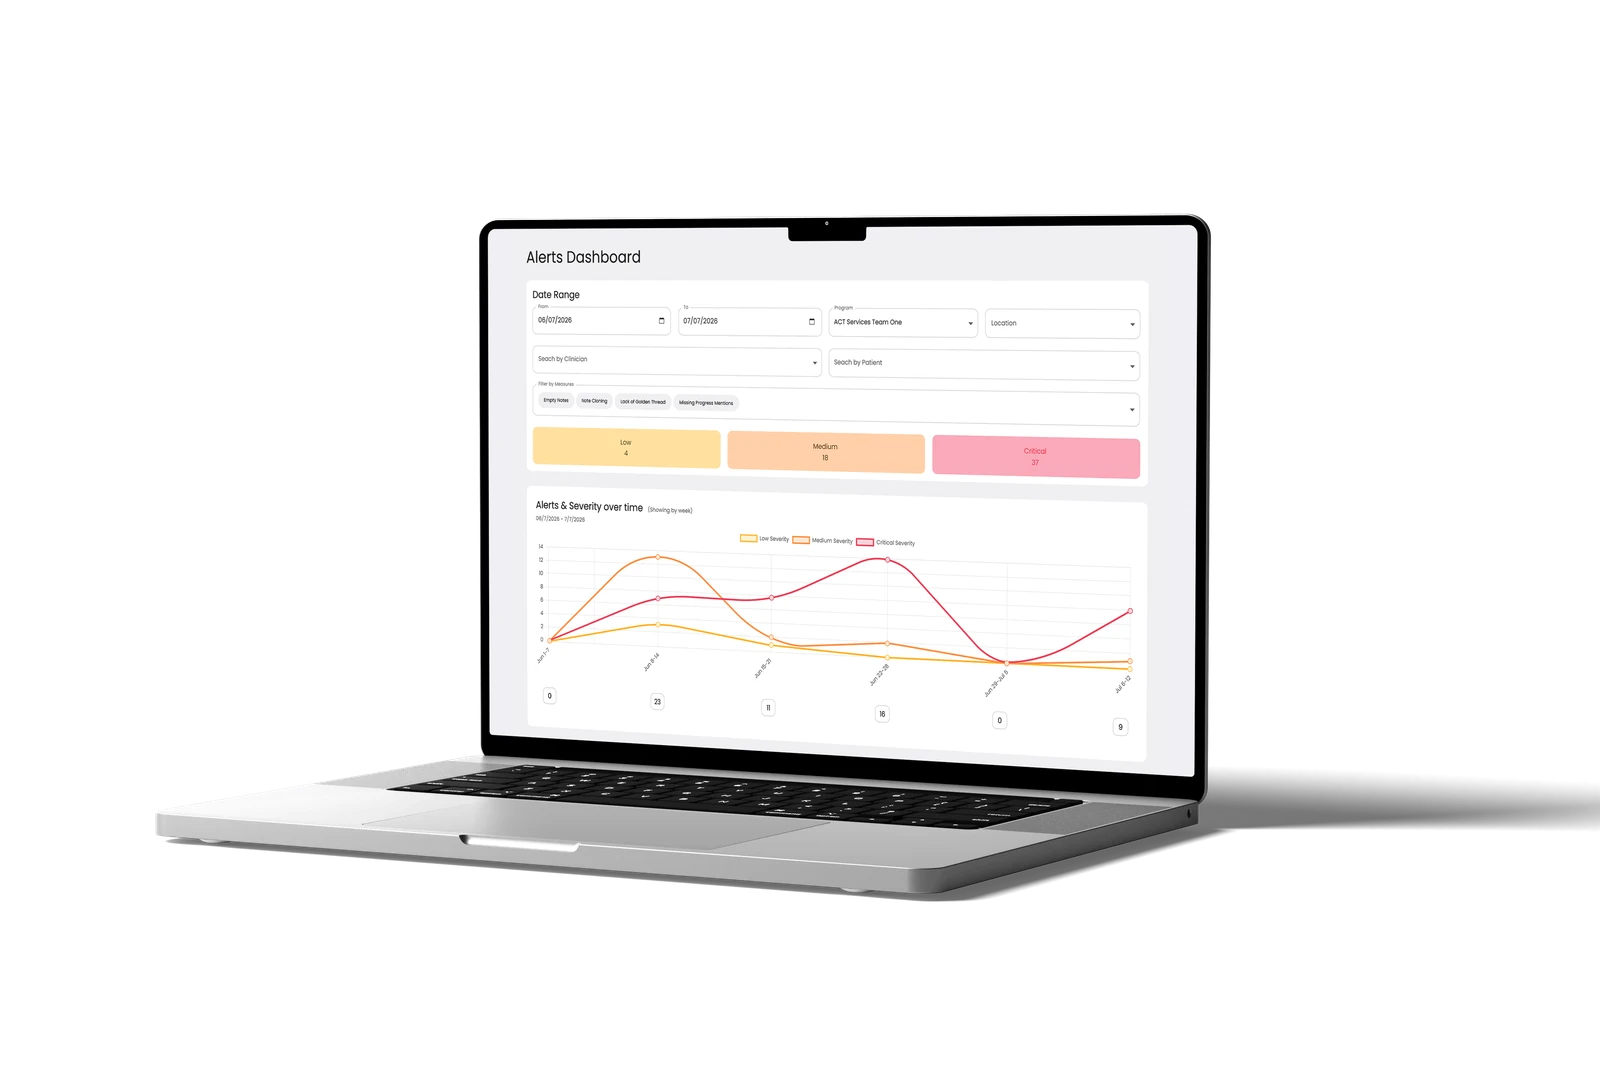
Documentation risk sorted by severity and tracked over time, filtered by program, location, clinician, and measure: empty notes, cloned notes, missing treatment-plan goals. Not a sample. The whole picture.
Human review, clinical judgment, and organizational oversight stay where they are.
This is not simply about writing notes faster. It is about protecting workforce capacity, strengthening care quality, and making sure the documentation behind care can withstand the scrutiny ahead.